
Framework overview: goals, constraints, and model choice
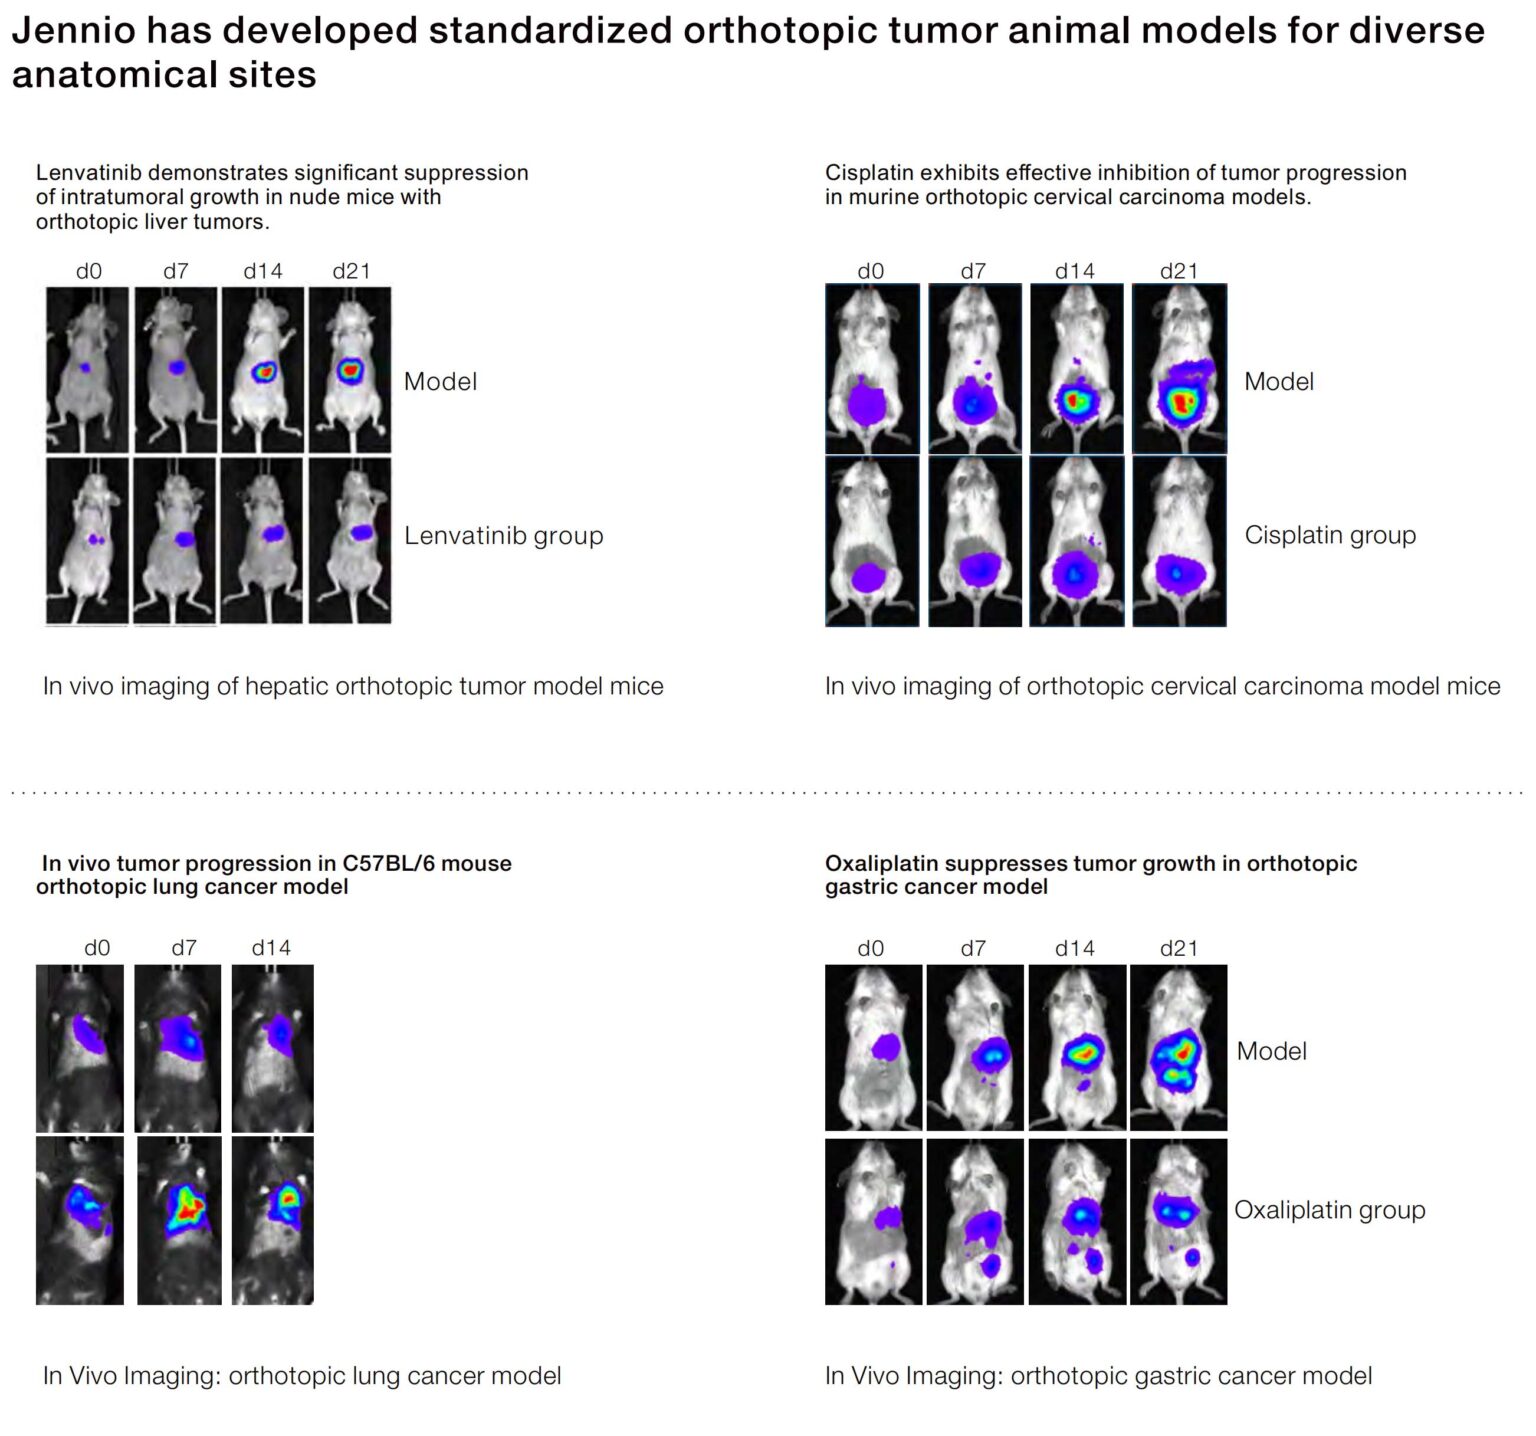
Designing a preclinical workflow begins with clear, testable goals—target engagement, tolerability thresholds, and translational endpoints—then maps resources and timelines against those goals. For solid-tumor programs this often means electing between orthotopic and ectopic placements; many teams choose an orthotopic tumor model to preserve the native tumor microenvironment and metastatic routes. Early choices about engraftment technique and immunocompetence determine downstream assays: a syngeneic orthotopic implantation supports immune readouts, whereas a patient-derived xenograft (PDX) emphasizes human tumor biology but limits immune profiling.
Core modules of the workflow
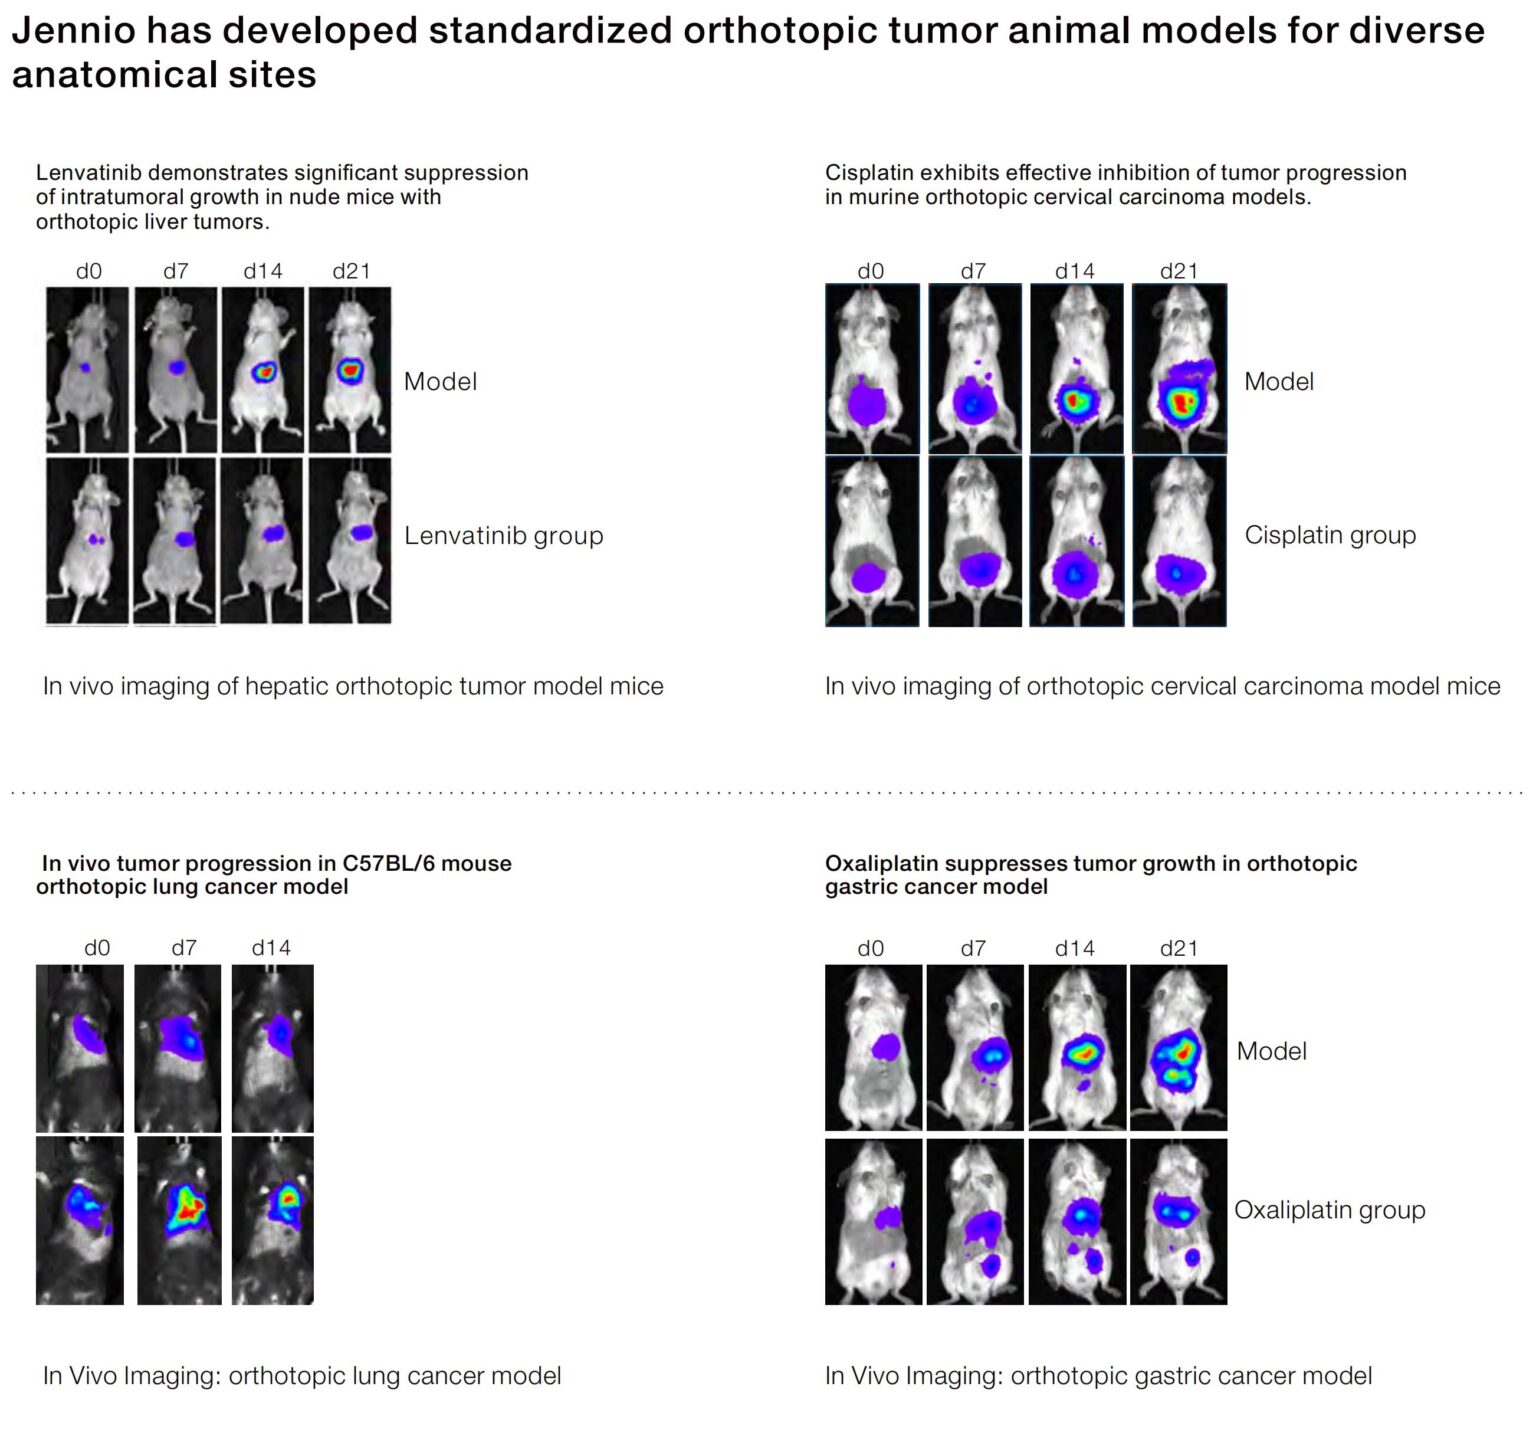
A robust framework divides the program into discrete modules so each team can iterate without derailing the whole project. Typical modules include: model qualification (xenograft validation, engraftment rates), dosing and PK/PD profiling (bioavailability windows, biomarker selection), efficacy readouts (tumor volume, survival, bioluminescence imaging), and pathology endpoints (IHC, stromal characterization). Keep acceptance criteria tight at module handoffs to avoid late-stage surprises. MD Anderson’s translational groups—known for integrating orthotopic implantation with immune assays—illustrate how early cross-talk between pathology and in vivo teams reduces rework.
Operational production teardown and practical controls
Break the operational production teardown into stepwise SOPs: animal sourcing, surgical implantation, peri-operative care, randomized dosing, and blinded endpoint analysis. Include explicit checkpoints such as acceptable engraftment percentage after 14 days and predefined imaging cadence. This section must also address database hygiene and reproducibility: record surgical logs, batch IDs, cage-level metadata, and necropsy photos. Operational notes should embed {main_keyword} and {variation_keyword} within task-level documentation so downstream analysts can trace outcomes to inputs.
Assays, readouts, and common pitfalls
Choose assays that align with the biology you need to measure. For invasive orthotopic models, bioluminescence imaging speeds longitudinal tracking; histology and IHC reveal microenvironment shifts. Beware common mistakes: over-reliance on a single tumor growth metric, insufficient power calculations, and inconsistent anesthesia protocols that alter physiology. Small technique differences—needle angle during orthotopic implantation or tumor fragment size in PDX—can change engraftment rates markedly. Plan for redundancy: dual readouts and a pathological audit at study end help validate crude tumor-volume signals.
Comparative considerations and alternatives
Compare orthotopic versus subcutaneous placements by endpoint needs. Subcutaneous models provide rapid, high-throughput tumor-volume data and simpler surgical needs; orthotopic or subcutaneous tumor model decisions should therefore be driven by study hypotheses—metastasis, local microenvironment, or pharmacology. Consider hybrid approaches: initial subcutaneous screens to triage candidates, followed by orthotopic confirmation in a smaller, rigorously powered cohort. This graded approach conserves resources while preserving translational fidelity.
Quality, reproducibility, and regulatory alignment
Embed quality controls and reproducibility metrics from day one. Use blinded scoring, randomized cage allocation, and prespecified statistical thresholds for primary endpoints. Capture exact test parameters—imaging exposure times, antibody clone IDs for IHC, and the 14-day engraftment cutoff used for cohort inclusion. Such specificity avoids ambiguous audit notes and aligns internal reports with external reviewers during IND-enabling discussions.
Advisory close: three critical evaluation metrics
When selecting study strategies or vendors, prioritize these three metrics: 1) biological fidelity—measured by metastatic incidence and molecular concordance to the source tumor; 2) operational reliability—tracked as percentage of cohorts meeting engraftment and imaging schedules; and 3) data traceability—complete metadata capture from surgery to pathology. Use these measures to compare platforms and to decide when a candidate advances.
Jennio Biotech has practical platforms and SOPs that reduce variability across those metrics, making translational decisions more straightforward. —